Hospital KPIs tell owners and managers whether beds, people and money are being used well, and where patients are waiting. The right handful, measured consistently and visible daily, will do more for a hospital than a hundred-page monthly MIS report nobody reads.
The trouble is that most hospitals either track too few numbers, usually just revenue and occupancy, or too many, without agreed definitions. Two managers quote different occupancy figures for the same month, and the meeting turns into an argument about the spreadsheet.
This guide lists the hospital KPIs worth tracking, with formulas and data sources, explains how to interpret them, and shows how to build a hospital dashboard that people actually open.
Why definitions matter more than charts
Before choosing KPIs, agree how each one is calculated. Bed occupancy sounds simple, but is a bed occupied if the patient was discharged at 10 am? Do day-care beds count? Is the ICU included? Different answers give different numbers, and none is wrong as long as everyone uses the same one.
For every KPI, write down:
- The formula, with numerator and denominator
- The data source in your hospital software
- The time period: day, week, month
- What is included and excluded, such as day care, ICU or newborns
- Who owns the number and acts on it
Bed and inpatient KPIs
Beds are the core economic unit of a hospital. These KPIs show how well they are used.
| KPI | Formula | What it tells you |
|---|---|---|
| Bed occupancy rate | Inpatient days in period ÷ (available beds × days in period) × 100 | How full the hospital is |
| Average length of stay (ALOS) | Total inpatient days ÷ number of discharges | How long patients stay |
| Bed turnover rate | Number of discharges ÷ available beds | How many patients each bed serves in the period |
| Bed turnover interval | (Available bed days − inpatient days) ÷ discharges | Average empty time between patients |
| Admissions per day | Total admissions ÷ days in period | Inflow trend |
High occupancy is not always good. Above a certain level, emergency admissions wait and elective surgeries get cancelled. Low ALOS is not always good either, if it comes with more readmissions. Read these KPIs together and by department, not as single hospital-wide numbers. Our guide to IPD and bed management software explains how bed status data feeds them.
Financial KPIs
Revenue alone hides a lot. These KPIs connect money to capacity.
| KPI | Formula | What it tells you |
|---|---|---|
| ARPOB (average revenue per occupied bed) | Inpatient revenue ÷ occupied bed days | Revenue earned per bed per day |
| Average revenue per OPD patient | OPD revenue ÷ OPD visits | Value of each outpatient visit |
| Payer mix | Revenue by payer type ÷ total revenue × 100 | Share of cash, insurance, schemes, corporate |
| Accounts receivable days | Outstanding receivables ÷ average daily revenue | How long you wait to be paid |
| Claim deduction rate | Deducted amount ÷ claimed amount × 100 | Insurance revenue lost |
| Discount percentage | Total discounts ÷ gross revenue × 100 | Leakage through discounts |
ARPOB is widely used by hospital chains because it combines pricing, case mix and length of stay into one figure. Some calculate it per day, some annualise it; pick one and stick with it. Insurance KPIs connect directly to the work covered in our post on TPA management in hospitals.
Patient flow and turnaround time KPIs
These are the KPIs patients feel. They also tend to reveal hand-off problems between departments.
- OPD waiting time: consultation start time minus registration or arrival time, as an average and 90th percentile
- Lab TAT: report authorised time minus sample collection time, by test category
- Radiology TAT: report finalised time minus scan completion time
- Emergency door-to-doctor time: first doctor assessment time minus arrival time
- Discharge TAT: time patient leaves minus time discharge order is written
- Bill-ready time: final bill ready minus discharge order time
- Bed allocation time: bed assigned minus admission decision
Use averages and the 90th percentile together. An average discharge TAT of two hours can hide a long tail of patients waiting five hours, and those are the ones who write reviews. The discharge process in hospitals guide shows how to break discharge TAT into its parts.
Clinical quality and safety KPIs
Clinical KPIs overlap with NABH quality indicators, and should use the same definitions. Common ones:
- 30-day readmission rate: readmissions within 30 days ÷ discharges × 100
- Return to ICU within 48 hours: ICU readmissions within 48 hours ÷ ICU transfers out × 100
- Surgical site infection rate: SSIs ÷ surgeries performed × 100
- Medication error rate: medication errors reported ÷ patient days × 1,000
- Mortality rate: deaths ÷ discharges including deaths × 100, ideally by department
- Patient falls: falls ÷ patient days × 1,000
Rates per 1,000 patient days let you compare months with different volumes. For accreditation-linked indicators, align with the definitions your quality team already uses, as discussed in our post on NABH compliant hospital management software.
Operations and staffing KPIs
A few operational numbers complete the picture:
- OT utilisation: actual surgical minutes ÷ scheduled theatre minutes × 100
- First case on-time start: first cases starting on time ÷ total first cases × 100
- Nurse-to-patient ratio by ward and shift
- Pharmacy stock-outs: number of items out of stock when requested
- Near-expiry stock value: value of stock expiring within 90 days
- Patient satisfaction or NPS from post-discharge feedback
Patient feedback is easiest to collect automatically, for example via a WhatsApp survey sent the day after discharge through your patient engagement tools.
Building a hospital dashboard people use
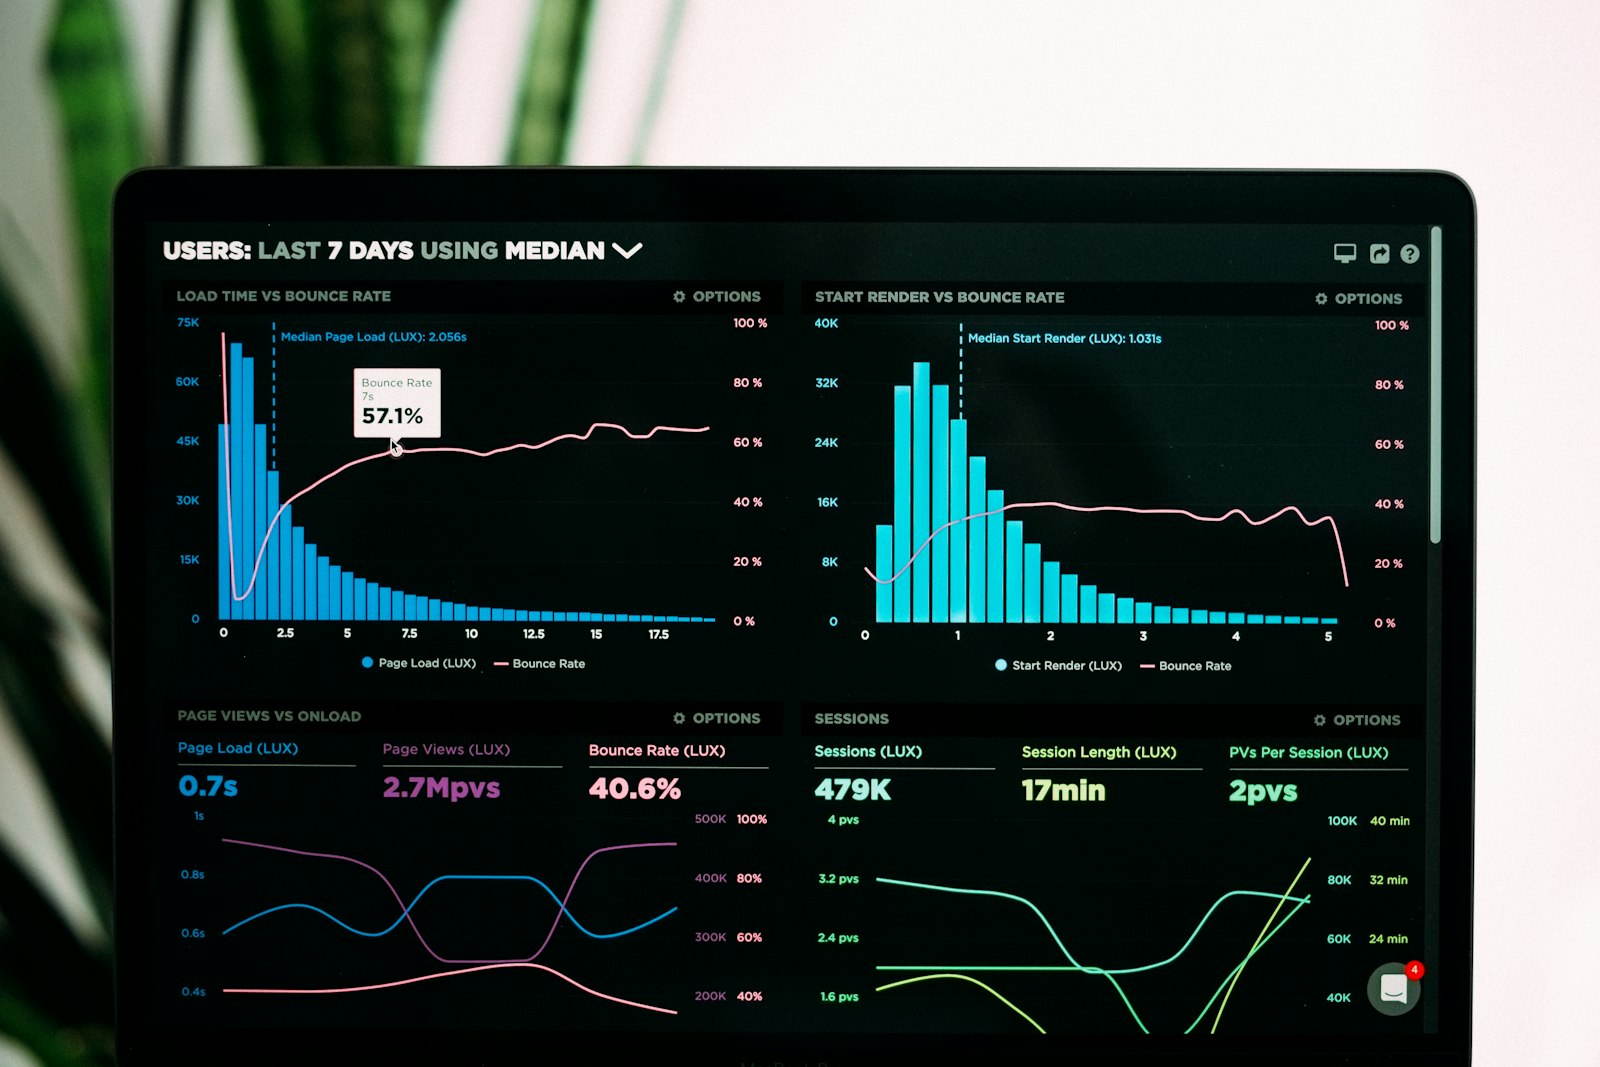
A hospital dashboard is useful only if it answers questions people actually ask, at the moment they ask them. Design it in layers.
- Owner view: five to eight numbers for today and this month, such as admissions, occupancy, revenue, collections, discharges pending, and alerts
- Department heads: their own KPIs with trends and comparisons with last month
- Operational screens: live queues, pending discharges, pending lab reports, empty beds
- Drill-down: every number clickable to the list of patients or bills behind it
Keep the owner view on one screen, readable on a phone. Use trends over the last 12 weeks rather than single numbers. Highlight only what needs attention, such as discharge TAT above target or a claim backlog older than 30 days.
Where the data comes from
All of these KPIs depend on timestamps and transactions in your hospital software: registration time, consultation start, order and result times, admission, bed transfer, discharge order, bill finalisation and payment. If your system does not capture these events, no dashboard tool will fix it.
Practical steps:
- Audit which timestamps your current system captures automatically
- Fix the gaps in workflows first, for example a "discharge order" action doctors actually use
- Build a reporting database or data warehouse so heavy queries do not slow the live system
- Validate each KPI against a manual count for one month before publishing it
Our health data analysis team usually starts with this audit, because it shows which KPIs are trustworthy today and which need workflow changes first.
Setting targets without inventing benchmarks
It is tempting to copy target values from a presentation or another hospital. Be careful: occupancy, ALOS and ARPOB vary widely by specialty mix, city, payer mix and hospital size. A cardiac centre and a general hospital will never look alike.
A better approach is to measure your own baseline for three months, set improvement targets against it, and compare departments with themselves over time. Where you do use external comparisons, make sure the definitions match.
A worked example: reading three KPIs together
Imagine a 120-bed hospital reviewing one month. Occupancy rose compared with the previous month, which looks like good news. But ALOS also rose, admissions per day stayed flat, and discharge TAT got worse. Read together, the story changes: the hospital is not treating more patients, it is keeping the same patients longer, partly because discharges are slow.
Drilling into discharge TAT by ward shows that most of the delay sits between the discharge order and the final bill on two surgical wards, and mostly for insured patients. The bill-ready time is long because pharmacy returns and consumable charges are closed only after the doctor writes the discharge order. Nobody owns that step.
The fix is operational, not technical: expected discharges are flagged the evening before, pharmacy returns are closed in the morning, and the insurance desk starts the final approval earlier. Over the next two months, discharge TAT on those wards falls, ALOS eases, and the hospital can admit more elective patients without adding beds, so ARPOB and revenue improve together.
No single KPI would have shown this. The value of a hospital dashboard comes from seeing related numbers side by side and being able to click through to the patients behind them.
Reviewing KPIs in a weekly rhythm
KPIs change behaviour only when they are discussed regularly. A short weekly operations review, thirty minutes with department heads, works well. Look at the owner view, pick the two numbers that moved the most, open the drill-down, and agree one action with a named owner for each. Next week, start by checking those actions. Monthly reviews can then focus on trends, targets and larger decisions such as staffing, pricing or capacity.
Conclusion
The best hospital KPIs are few, clearly defined, owned by someone, and visible while there is still time to act. Start with occupancy, ALOS, ARPOB, discharge TAT, lab TAT, receivable days and a few quality indicators. Make sure your software captures the timestamps behind them, then build a layered hospital dashboard that owners can read on a phone.
Algon builds owner dashboards into the hospital management system projects we deliver, drawing on events captured as staff work. If you want a dashboard you can trust, contact us.
Frequently asked questions
What are the most important hospital KPIs?
Bed occupancy, average length of stay, ARPOB, OPD waiting time, discharge turnaround time, lab TAT, accounts receivable days, claim deduction rate, readmission rate and patient satisfaction are a strong core set for most hospitals.
How is ALOS calculated?
Average length of stay is total inpatient days in a period divided by the number of discharges in that period. Decide upfront whether to include day care and how to count same-day admissions.
What is ARPOB in hospitals?
Average revenue per occupied bed. It is inpatient revenue divided by occupied bed days, showing how much revenue each occupied bed earns per day.
How do you calculate bed occupancy rate?
Divide inpatient days in the period by the number of available beds multiplied by days in the period, then multiply by 100 to get a percentage.
What should a hospital owner dashboard show?
A small set of numbers for today and this month, such as admissions, occupancy, revenue, collections, pending discharges and alerts, with trends and drill-down to the patients or bills behind each figure.
What is a good bed occupancy rate for a hospital?
It depends on specialty mix, emergency load and size. Very high occupancy can cause admission delays. Measure your own baseline and set targets by department rather than copying a single benchmark.